
Beyond the Binding Pocket: What Makes a Drug Target “Druggable”?
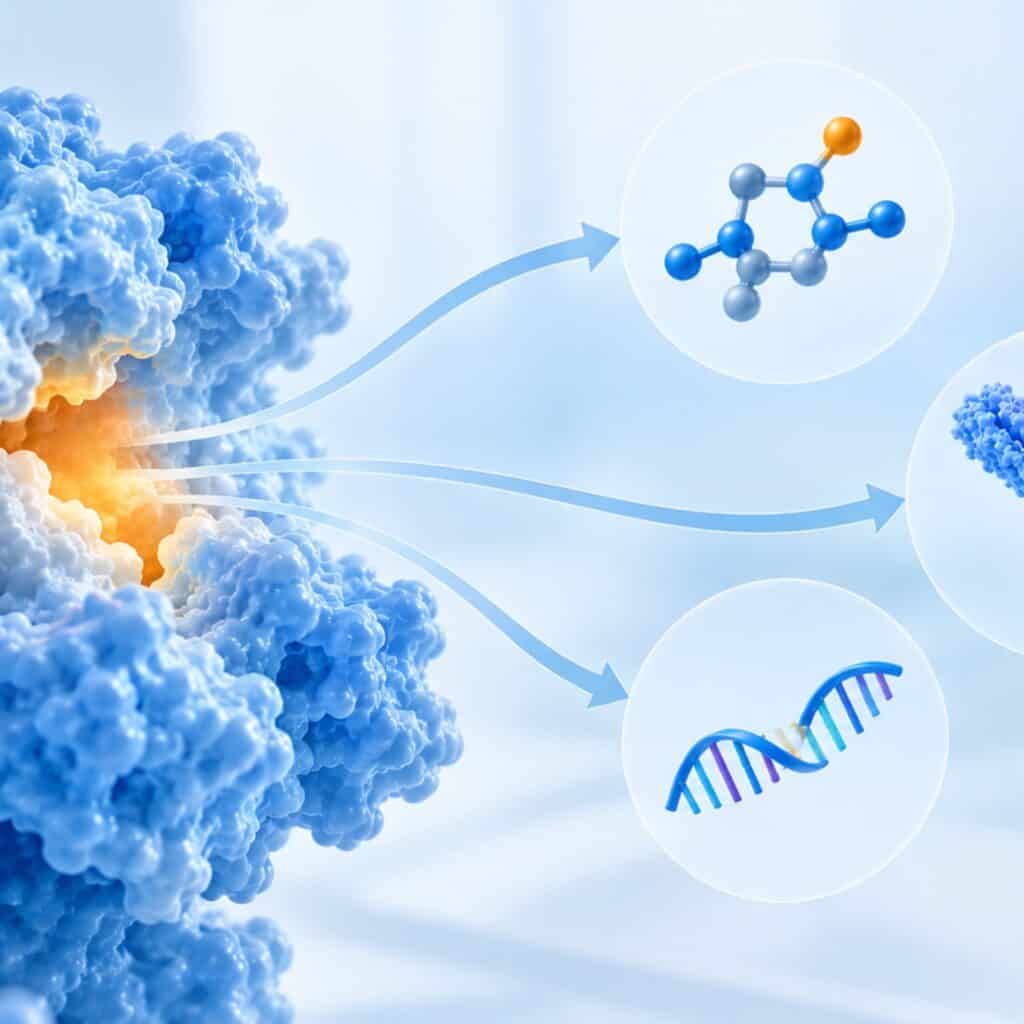
Identifying a target that matters in a disease is indeed an important milestone, but drug discovery doesn’t end there. In fact, identification is only an opening gambit. A protein may show a strong genetic profile, expression data, or disease models, yet still prove difficult to turn into something that will actually help patients. Rigor in confirming this characteristic early is foundational, and it shapes some of the most consequential decisions in a program’s discovery path.
What is Druggability?
Druggability is defined as “the likelihood that a target can be engaged by a therapeutic modality with enough potency, selectivity, suitable pharmacological behavior, and safety to support development.” In other words, the question is whether the target can be therapeutically modulated in a way that produces the desired biological effect with an acceptable safety profile.
Historically, drug development often focused on whether a small molecule could bind to a suitable binding site (i.e., pocket) on a target protein. Today, the question is more complex. Scientists need to know which modality, biological context, and evidence will make the intended target most amenable to therapeutic intervention. The early pocket-focused view, however, laid the foundation for today’s breakthroughs in drug development.
Druggability Began with the Binding Pocket
The most tractable targets in modern drug discovery were traditionally enzymes, receptors, and related proteins with well-defined pockets. Small molecules would enter these pockets and modulate their targets based on the drug’s development plan. The basis of structural druggability is that the target must provide an accessible binding site with the dimensions and chemical features required to support strong and selective binding.
The BCR-ABL fusion protein offers a good illustration of this model. BCR-ABL is formed when parts of the BCR and ABL1 genes join and is found in most people with chronic myelogenous leukemia. Its chromosomal abnormality illustrated chronic myeloid leukemia at the genetic level, while its kinase domain cleared a route for small-molecule inhibition. Imatinib, for example, inhibits BCR-ABL kinase activity by binding its inactive form and blocking ATP binding. This pocket-based model is valuable, but incomplete. Many of the disease-relevant proteins seen today lack such deep binding pockets and possess more complex biology. The main problem is that a target may be biologically compelling—i.e., it establishes genetic association, abnormal expression, or a promising phenotypic screening result—but can still resist contemporary drug design.
Disease Relevance is Necessary, but Insufficient
Target validation and druggability answer different questions. Target validation is about whether a protein contributes meaningfully to disease biology. Druggability, on the other hand, seeks a therapeutic intervention that can selectively, safely, and effectively modulate the protein.
A practical assessment of druggability comprises three dimensions:
- Structural druggability: Does the target present an accessible pocket, epitope, or other physical opportunity for intervention?
- Modality-related druggability: Can a small molecule, antibody, peptide, degrader, or nucleic-acid therapy engage it?
- Biological and translational context: Is the target expressed and accessible in the relevant tissue or cell type, and can it be modulated in a way that supports the desired biological effect and an acceptable therapeutic window?
Selectivity, tissue access, target location, and therapeutic window should, therefore, be considered essential components of an assessment rather than details to be addressed later. Doing so helps advance therapeutic technology and change what is considered possible.
When ‘Undruggable’ Becomes Outdated
KRAS is one of the industry’s clearest examples of how druggability can change. RAS proteins lack high-quality binding pockets and usually bind GTP with high affinity. Therefore, they were considered poor targets for conventional small molecules. That all changed when scientists identified a previously unrecognized pocket in the KRAS G12C mutant. They found that covalent inhibitors can exploit the mutant cysteine and stabilize KRAS in an inactive state. In other words, what was once undruggable became druggable. This advance led to approved therapies for KRAS G12C-mutant non-small cell lung cancer. That does not make every KRAS variant equally amenable to target therapies, but it does demonstrate what can happen when the tools, information, and modality advance.
Alternative modalities can also dramatically change an assessment. While new modalities cannot eliminate risk altogether, they can shift development questions toward delivery, selectivity, durability, safety, and manufacturability. For example, antibodies can target extracellular or cell-surface targets, while degraders and molecular glues can remove a disease-driving protein rather than merely inhibit its activity. Moreover, RNA-directed, cell-based, and gene-based approaches can broaden the range of options for biological mechanisms that are poorly suited to standard small-molecule binding.
Rather than viewing targets as simply “druggable” or “undruggable,” druggability is increasingly considered in the context of the available therapeutic modality, biological setting, and evolving scientific evidence.
‘Druggability’ is an Evolving Question
Druggability is not a structural score or binary label assigned at the beginning of a program. Instead, it is better thought of as a dynamic body of evidence. For example, binding pockets are important, but we know now that they are only one part of a biological assessment. Protein interactions, tissue distribution, pathway roles, and disease-specific expression can all affect whether an intervention is possible and meaningful. Further research into protein forms, interactions, and tissue context may also illuminate new pathways. Specifically, proteomics can characterize low-abundance proteins, proteoforms, and dynamic protein interactions, potentially exposing a host of new therapeutic opportunities.
Drug development teams should therefore revisit druggability as data, screening, disease models, biomarkers, and modalities evolve. This approach supports smarter target prioritization, fit-for-purpose assay design, and screening strategies. Importantly, it also helps teams avoid committing significant resources to mechanisms unlikely to result in a safe and effective drug.
A Final Word on Druggability
As drug discovery moves toward less accessible enzymes and receptors, druggability must become a disciplined question. We know a well-validated target doesn’t always mean a druggable one, but a challenging target may now be within reach. A comprehensive assessment of a target being considered for advancement cannot rely on a single characteristic, such as a binding pocket. Expanding our concept of what is druggable will require better biological insight and modalities, not simply more targets.
You May Also Be Interested In


Discuss Your Program with Us
Share your development goals and key challenges with our experts to define the right path forward.